
Introduction
Prostate cancer (PCa) is the second most frequent neoplasm in men in the world, accounting for over 1.4 million new cases in the United States, and the prevalence of men living with it is expected to be over 5 million by 2027.1,2 It’s the most common male cancer and the most common cause of cancer death in Latin America1. In Colombia, it occupies second place in the general population, with an incidence of 12.5%. Considering only the male population, the highest incidence is for PCa (21.7%), followed by lung cancer (16.9%).2
Mortality varies according to the territory. In Colombia, it is estimated that the incidence of PCa has an age-adjusted rate of 49.8/100,000 men and an age-adjusted mortality rate of 12/100,000 men.3
Approximately 79% of PCa patients are diagnosed with localized disease. Radiation therapy (RT) is one of the most important therapeutic mainstays of clinically localized PCa. However, the optimal fractionation and total treatment time for irradiation is still under debate. Conventionally, it is applied by fractions of between 1.8 and 2.0 Gy, 5 days/week for 8-9 weeks. The total dose administered is usually 70-80 Gy.4,5
A landmark discovery in radiation biology was made in the 1980s, and was the recognition of a systematic difference between the dependence of normal tissue fractionation on acute and late reaction. Late reactions are much more dependent on the size of the dose fraction than are acute reactions. The radiobiological model suggests that PCa has a low alpha/beta ratio (< 1.5-1.8), which allows to significantly increase the effective biological dose received by the tumor, thus obtaining better response rates, and decreasing the number of treatment sessions (hypofractionated radiotherapy).4,6
In 1999, Brenner and Hall suggested that the accepted argument that multiple dose fractions would reduce toxicity to late responding tissues for a given tumor control may not necessarily apply to PCa, possibly because most prostate tumors grow very slowly.4,7 This finding eliminated the advantage conferred to multiple-dose fractions and led to the suggestion that if the sensitivity to fractionation is the same for tumor and surrounding normal late-responder tissue, one would expect a much smaller number of fractions (with an appropriately reduced dose) to be at least as effective, but with benefits from a logistical and financial standpoint. This technique of using smaller amounts of larger dose fractions is known as hypofractionation of PCa,4 which is based on the administration of higher doses per fraction over a smaller number of fractions, achieving a lower total dose than conventional fractionated RT. With hypofractionated RT, a single fraction ≥ 2.1 Gy is applied, 4 or 5 days/week, for 4-5 weeks. The total radiation dose in hypofractionated RT varies between 52.5 and 72 Gy. The use of this new technique would be justified by the fact of the dose-response relationship and a high sensitivity to the dose per fraction applied, improving tumor control and reducing radiation-induced toxicity, in addition to optimizing resources, reducing costs, and improving the patient’s quality of life.1,5
However, the literature shows contradictory results regarding its efficacy and safety when comparing conventional and hypofractionated radiotherapy.6–8
In Latin America, there are no studies describing genitourinary and gastrointestinal toxicity, quality of life, and survival in patients who receive hypofractionated therapy. Since PCa is one of the tumors with the highest incidence in the country, it is necessary to better characterize these outcomes in the Colombian population to define strategies that have a significant impact on them.
The increase in diagnosis in early stages, associated with similar life expectancies among the different treatments, creates a challenge for both patients and treating physicians in choosing the best therapeutic option. One of the fundamental aspects in making this decision is the impact that the treatment has on the quality of life and treatment-related symptoms.
The objective of this study is to evaluate the impact on acute and late genitourinary and gastrointestinal toxicity as a primary outcome, as well as on sexual, bowel, and urinary quality of life as a secondary outcome using patient reported outcomes measures (PROMS) in patients with localized PCa treated with hypofractionated radiotherapy in the population of Bogota, Colombia, managed in a high complexity hospital.
Materials and methods
Study design and participants
A prospective cohort study was performed. All patients with localized PCa of low, intermediate, or high risk treated with hypofractionated RT, with or without hormonal blockade, and followed up at the Xavierian Oncology Center of San Ignacio University Hospital were included in the study. The patients were collected from September 01, 2020, when the hypofractionation protocol was initiated at the aforementioned institution, until December 31, 2022. A convenience sampling of all patients treated with hypofractionation in the RT service was performed.
The present project complies with and follows the “Scientific, Technical and Administrative Standards for Health Research” established in Resolution 8430 of 1993 of the Ministry of Health. The research was considered not to represent a risk for the participants in accordance with Article 11 of Resolution 8430 of 1993 of the Colombian Ministry of Health. Nevertheless, the study was conducted under the parameters established in national and international regulations, following the recommendations established in the Declaration of Helsinki. The study was approved in the Institutional Research and Ethics Committee of the Faculty of Medicine of the Xavierian Pontifical University and the San Ignacio University Hospital. All patients provided written informed consent. Participants did not receive compensation for joining the study, and no commercial support was provided.
Outcomes
The main outcomes measured were acute and late genitourinary and gastrointestinal toxicity with the RT Oncology Group (RTOG) scale at 14 days, 3 months, and 1 year after the end of RT, as well as sexual, intestinal, and urinary quality of life using PROMS. The Expanded Prostate Cancer Index Composite (EPIC) for Clinical Practice and the Short-Form 12 (SF-12) surveys provide a clinically relevant and validated tool in Spanish to assess and quantify the side effects of RT. These outcomes were measured at baseline (before initiating RT), 3 months, 6 months, and 1 year after completion of RT.
In addition, as secondary outcomes, oncologic outcomes were measured in terms of overall survival, Biochemical relapse-free survival, and metastasis-free survival at 3-month, 6-month, and 1-year follow-up after completion of RT. Biochemical relapse was defined as an elevation of prostate-specific antigen > 2 ng/mL above the nadir in 3 consecutive measurements.
The presence of metastases was defined by conventional imaging (abdominal computed tomography and bone scan) at follow-up.
Procedure
Radiotherapy dose prescription was determined according to the National Comprehensive Cancer Network guidelines risk group, following institutional protocol: Low Risk – 60 Gy in 20 fractions; Intermediate and high risk 20 fractions with dose per day of 2.4 Gy and 3 Gy with integrated boost up to 48 Gy in PTV_48 Gy, and up to 60 Gy in PTV_60 Gy.
Radiotherapy treatment was planned with the volumetric modulated arc therapy technique.
Statistical analysis
Data were processed in the statistical program STATA (version 14, StataCorp, College Station, TX, USA). Descriptive analysis was performed. Frequency and percentage tables were used to summarize categorical data. For continuous data, the normality distribution was analyzed using the Shapiro–Wilk test. For variables with normal distribution, measures of central tendency such as mean and standard deviation were used; for variables that did not meet this distribution, the median and interquartile range were used. The Kaplan-Meier method was used to estimate overall, relapse-free, and metastasis-free survival. The central limit theorem was applied for the distribution of the data of the quality of life scales with normal distribution; a paired t-test was used to compare and perform the statistical analysis of the quality of life score at baseline, 3 months, 6 months, and 1 year after the end of treatment. For quality of life data without a normal distribution, a Wilcoxon Signed-rank test was used to compare the baseline quality of life score at 3 months, 6 months, and 1 year after completion of treatment. Given the sample size, multivariate models were not used.
Results
Between September 2020 and December 2022, 176 patients with localized PCa treated with RT at the Xavierian Oncology Center were included. The most frequent risk group according to D’Amico classification was high, with 84 patients (47.7%). 27 patients with locally advanced stage were included. The mean follow-up time was 9.33 months (range 0.73-27).
The baseline characteristics of the included patients are listed in table 1.
Table 1. Baseline characteristics
| Characteristic | n (%) |
|---|---|
| Age – mean (range) (years) | 69.96 (51-84) |
| BMI – mean (range) (kg/m2) | 24.85 (17-35) |
| T (Tumor) 1A 1B 1C 2A 2B 2C 3A 3B 4 X | 2 (1.13)2 (1.13)47 (26.70)31 (17.61)30 (17.00)17 (9.65)31 (17.61)6 (3.40)6 (3.40)4 (2.27) |
| N (node) 0 1 X | 78 (44.3)15 (8.5)83 (47.1) |
| PSA – mean (range) (ng/mL) | 37.09 (3-291) |
| ISUP grade group 1 2 3 4 5 | 33 (18.75)40 (22.72)39 (22.15)52 (29.54)12 (6.81) |
| D’Amico risk group Low Intermediate High | 13 (7.38)52 (29.54)84 (47.72) |
| Hormone blockage Yes Pharmacological Surgical No Follow-up (months) | 144 (81.81)141 (97.91)3 (2.08)32 (18.18)9.33 (0.73-27) |
|
BMI: body mass index PSA: prostate specific antigen; ISUP: International Society of Urological Pathology. |
|
One hundred and forty-six patients (82.9%) completed the 3-month follow-up, 116 (65.9%) completed the 6-month follow-up, and 91 (51.7%) completed the 1-year follow-up.
Before the start of RT, the mean physical score on the SF-12 health questionnaire was 48.0, at 3-month follow-up after completion of RT was 47.3, at 6-month 47.2, and at 1-year 46.5. While the mean mental score for the same questionnaire before the start of RT was 49.6, at 3 months follow-up after completion of RT was 49.5, at 6 months 49.2, and at 1 year 52.9 (Table 2).
Table 2. Comparison of physical and mental scores of the SF-12 health questionnaire at baseline, 3 months, 6 months, and 1 year after completion of RT
| SF- 12 physical score | Mean (range) | Standard deviation | Confidence interval (95%) | p |
|---|---|---|---|---|
| Baseline | 48.0 (32.3-63.5) | 6.4 | 46.7-48.8 | 0.43 |
| 3 months | 47.3 (30.5-62.6) | 6.4 | 46.3-48.4 | 0.43 |
| 6 months | 47.2 (30.5-62.6) | 6.3 | 46.0-48.4 | 0.04 |
| 1 year | 46.5 (38.8-50.8) | 4.3 | 41.6-50.9 | 0.16 |
| SF- 12 mental score | ||||
| Baseline | 49.6 (27.9-65.1) | 7.4 | 48.6-51.0 | 0.30 |
| 3 months | 49.5 (27.9-65.1) | 7.5 | 48.3-50.7 | 0.30 |
| 6 months | 49.2 (27.9-61.3) | 7.6 | 47.8-50.6 | 0.42 |
| 1 year | 52.9 (41.2-60.5) | 7.1 | 45.2-60.7 | 0.92 |
|
SF-12: short-form 12, RT: radiation therapy. |
||||
For the EPIC-26 questionnaire, in the urinary incontinence domain before the start of RT an mean score of 69.8 was obtained, at 3 months follow-up after completion of RT, it was 69.4, at 6 months 66.9, and at 1 year 79.6. In the urinary symptoms domain, before the start of RT, the mean score was 71.4, at 3-month follow-up after completion of RT was 71.1, at 6 months 69.4, and at 1 year 83.6. In the bowel function domain, before the start of RT, the mean score was 85.7, at 3 months follow-up after completion of RT, it was 85.3, at 6 months, 84.4, and at 1 year, 86.5. In the sexual function domain, before the start of RT, the mean score was 43.0, at 3 months follow-up after completion of RT was 42.6, at 6 months 42.2, and at 1 year 47.8. In the hormonal symptoms domain, before the start of RT, a mean score of 85.6 was obtained, at 3 months follow-up after completion of RT was 85.1, at 6 months 84.0, and at 1 year 71.8 (Fig. 1).
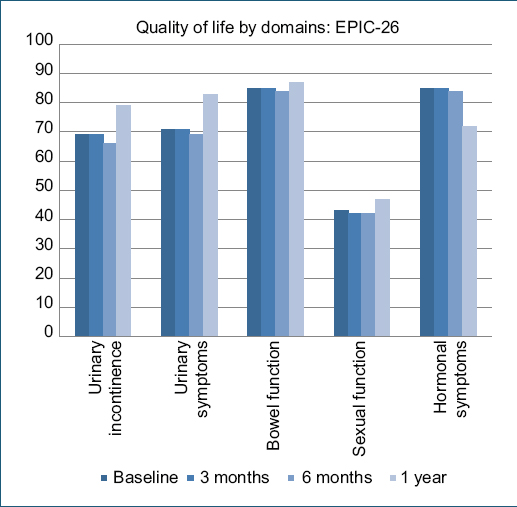
Figure 1. Comparison of quality of life according to domains of the expanded prostate cancer index composite-26 questionnaire at baseline, 3 months, 6 months, and 1 year.
In the RTOG urinary toxicity classification, it was found at 14 days that 40.9% reported a score of 0, 28.4% reported a score of 1, 25.0% reported a score of 2, 1.7% reported a score of 3, and 3.9% reported a score of 4. At 3 months, 38.2% reported a score of 0, 23.4% reported a score of 1, 33.9% reported a score of 2, 4.3% reported a score of 3, and no patients reported a score of 4 (p = 0.26). At 1 year, 15.6% reported a score of 0, 55.3% reported a score of 1, 29.1% reported a score of 2, and no patients reported a score of 3 or 4 (p = 0.18) (Fig. 2).
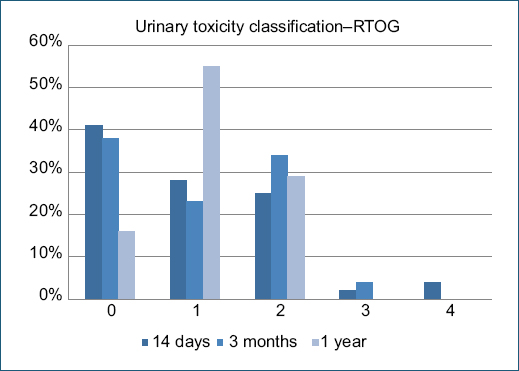
Figure 2. Comparison of urinary toxicity by radiation therapy oncology group classification at 14 days, 3 months, and 1 year after radiotherapy.
In the RTOG rectal toxicity classification, it was found at 14 days that 64.7% reported a score of 0, 15.9% reported a score of 1, 1.7% reported a score of 2, 17.0% reported a score of 3, and 0.5% reported a score of 4.
At 3 months, 80.0% reported a score of 0, 8.7% reported a score of 1, 1.7% reported a score of 2, 9.5% reported a score of 3, and no patients reported a score of 4 (p = 0.26). At 1 year, 53.4% reported a score of 0, 44.3% reported a score of 1, 2.3% reported a score of 2, and no patients reported a score of 3 or 4 (p = 0.13) (Fig. 3).
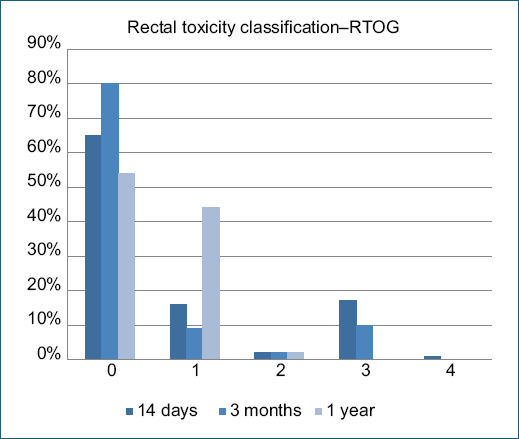
Figure 3. Comparison of rectal toxicity by radiation therapy oncology group classification at 14 days, 3 months, and 1 year after radiotherapy.
1 patient died 6 months after completion of RT due to a COVID-19 respiratory infection. No deaths associated with PCa were documented. There was no biochemical relapse in any case. No metastases were documented during follow-up.
Discussion
The safety of hypofractionated RT is considered a fundamental aspect due to the proximity of healthy tissues, such as the rectum and bladder, in the area to be irradiated.
The review by Botrel et al.9 showed that the incidence of grade ≥ 2 acute gastrointestinal toxicity was higher in the hypofractionated RT group with a RR of 2.02. Acute genitourinary toxicity (grade ≥ 2) was similar in both groups, with a RR of 1.19, both with moderate heterogeneity. In the long term, the incidence of gastrointestinal toxicity was similar in both groups with RR of 1.17. The incidence of long-term genitourinary toxicity was also similar in both groups with a RR of 1.16.
The review by Zaorsky et al.10 showed that acute toxicity was similar in the 2 groups in 3 of the 5 included studies. While the other two studies find a significantly higher rate of gastrointestinal toxicity in the hypofractionated RT group between weeks 2 and 4.
In summary, the two systematic reviews show no significant differences in the occurrence of genitourinary toxicity between the two treatments. However, they did find a high rate of acute gastrointestinal toxicity in patients treated with hypofractionated RT in one of the systematic reviews; it is important to mention that the authors of this review state that among the limitations is the small number of studies included in the review, and therefore consider it necessary to carry out additional research.
The Cochrane meta-analysis by Hickey et al. concluded that moderate hypofractionation has similar oncologic outcomes of disease-specific disease-free survival, overall survival, and metastasis-free survival compared to conventional fractionation, with no increase in late toxicity, but with a likelihood of increased acute gastrointestinal toxicity.11
Regarding the long-term toxicity of hypofractionated RT, there is a limitation due to the lack of information on prolonged follow-up periods. Most of the available studies include as late complications those that appear or persist 6 months after the end of RT. One study with a 5-year follow-up found that hypofractionation has limited long-term Grade 2-3 complications. However, the authors are cautious due to the limitations of the study (single center, single hypofractionation regimen, and limited number of cases).12
The three largest studies, PROFIT, CHHiP, and NRG 0415, have demonstrated non-inferiority of moderate hypofractionation schedules for localized PCa with respect to disease control, physician-reported toxicity, and PROMS at 5 years.13–15
In the PROFIT study 1,206 men with intermediate-risk PCa were randomized to conventional RT (78 Gy in 39 fractions) or hypofractionated RT (60 Gy in 20 fractions over 4 weeks). With a median follow-up of 6 years, hypofractionated RT was found to be non-inferior with respect to biochemical relapse-free survival (hazard ratio [HR] 0.96, 90% confidence interval [CI] 0.77-1.2). An increase in acute gastrointestinal toxicity grade > 2 was observed in the hypofractionated RT group. However, it was not associated with increased late toxicity; in fact, a lower rate of late grade > 2 gastrointestinal toxicity was reported in the hypofractionated RT group.13
In the CHHiP study, patients were randomized (1:1:1) to conventional (74 Gy) or hypofractionated RT with intensity modulated techniques. The median follow-up was 62.4 months. The proportion of patients who were free of biochemical or clinical relapse at 5 years was 88.3% in the conventional RT group and 90.6% in the 60 Gy hypofractionated RT group. Using the EPIC-26 and SF-1 questionnaires, an earlier manifestation of gastrointestinal and genitourinary toxicity symptoms was found in the hypofractionated RT group (4-5 weeks vs. 7-8 weeks). In addition, a higher grade > 2 acute gastrointestinal toxicity was found in the hypofractionated group (38% vs. 25%). Gastrointestinal and genitourinary toxicity was similar in both groups at 18 weeks and at 5 years. The 5-year cumulative incidence of RTOG grade ≥ 2 intestinal and genitourinary adverse events was 13.7% and 9.1% in the 74 Gy fraction group, 11.9% and 11.7% in the 60 Gy group, 11.3% and 6.6% in the 57 Gy group, respectively.14
The NRG Oncology 0415 trial randomized 1,092 men with low-risk CaP to conventional (73.8 Gy in 41 fractions) or hypofractionated (70 Gy in 28 fractions) RT. With a median follow-up of 5.8 years, the hypofractionated group was found to be non-inferior in disease-free survival (HR 0.85; 95% CI 0.64-1.14). In contrast to the CHHiP and PROFIT study, an increase in grade > 2 late gastrointestinal toxicity was reported in the hypofractionated RT group; however, it has been observed that this program had a higher biological effective dose than the conventional RT group (128 Gy vs. 118 Gy), assuming an a/b ratio of 3 Gy to the rectum and bladder.15
In our study, we found that the overall quality of life in physical score measured by the SF-12 questionnaire presented a statistically significant decrease of 0.8 points between the baseline measurement and at 6 months after the end of radiotherapy, while at 3 months and 1 year, no statistically significant differences were found. In the mental score, an increase of 3 points was found at 1 year of follow-up with respect to the baseline score; however, no statistically significant differences were found in the score at any cut-off point.
Regarding quality of life assessed by the EPIC-26 questionnaire, at 1 year, there was an increase of 9.8 points in urinary incontinence, 12.2 points in urinary symptoms, and 0.8 points in bowel function compared with baseline. In contrast, sexual function decreased by 4.8 points and hormonal symptoms decreased by 13.8 points at 1 year. However, no statistically significant differences were observed at any time point across all domains.
Acute urinary toxicity (RTOG) at 14 days was absent in 40.91% of patients, mild in 28.41%, and severe in 30.68%. At 3 months, 62.06% had no toxicity, and 37.93% had mild toxicity, with no severe cases. At 1 year, late urinary toxicity was mild in 84% and absent in 15%, with no severe events.
Acute rectal toxicity (RTOG) at 14 days was absent in 64.77% and severe in 19.32% of patients. At 3 months, 80.17% had no toxicity, and 11.20% had severe toxicity. At 1 year, late rectal toxicity was absent in 53.4% and mild in 46.6%, with no severe cases. No statistically significant differences were observed in acute or late urinary or rectal toxicity.
A systematic review by Sánchez-Gómez et al.16, describes, within its efficacy results, the meta-analysis by Botrel et al., which shows that biochemical relapse-free survival is similar in the conventional and hypofractionated radiotherapy group with an HR of 1.03 (95% CI: 0.88-1.20; p = 0.75); however, with high heterogeneity. The biochemical relapse rate is similar between both groups, with a relative risk (RR) of 0.99 (95% CI: 0.87-1.12; p = 0.85) with moderate heterogeneity. The cancer mortality rate does not differ in both groups with RR of 0.34 (95% CI: 0.09-1.23; p = 0.1).9
The results of the systematic review by Zaorsky et al.10 show significant differences in biochemical relapse-free survival in two studies, one in favor of conventional RT (60% versus 53%) and the other in favor of hypofractionated RT (79% versus 85%) (p = 0.035).
In our study, no cases of PCa-associated mortality were found, and no biochemical relapse or metastasis was documented during follow-up in any case.
As limitations of our study, we found a reduced population at 1 year of follow-up, which was our last cut-off point, and a short follow-up time.
Conclusion
Studies performed since the introduction of hypofractionation have shown that although it is not superior to the conventional RT, it is not inferior to it in terms of biochemical control, with similar cancer-specific and overall survival rates for both groups; however, due to the described quality and limitations of these studies, we can consider that there are no conclusive results on the safety of hypofractionated RT in the treatment of PCa in terms of toxicity, being the lack of evidence on long-term results one of the main limitations for the hypofractionated option to be considered the standard of treatment. Our study shows that there are no statistically significant differences in general and domain-specific quality of life, as well as for acute and late genitourinary and gastrointestinal toxicity up to 1 year of follow-up, with promising results in terms of oncologic outcomes.
Funding
The authors declare that this work was carried out with the authors’ own resources.
Conflicts of interest
The authors declare that they have no conflicts of interest.
Ethical considerations
Protection of human subjects and animals. The authors declare that no experiments on humans or animals were performed for this research.
Confidentiality, informed consent, and ethical approval. The authors have followed their institution’s confidentiality protocols, obtained informed consent from all patients, and secured approval from the Ethics Committee. SAGER guidelines have been followed as applicable to the nature of the study.
Declaration on the use of artificial intelligence. The authors declare that no generative artificial intelligence was used in the writing or creation of the content of this manuscript.
